
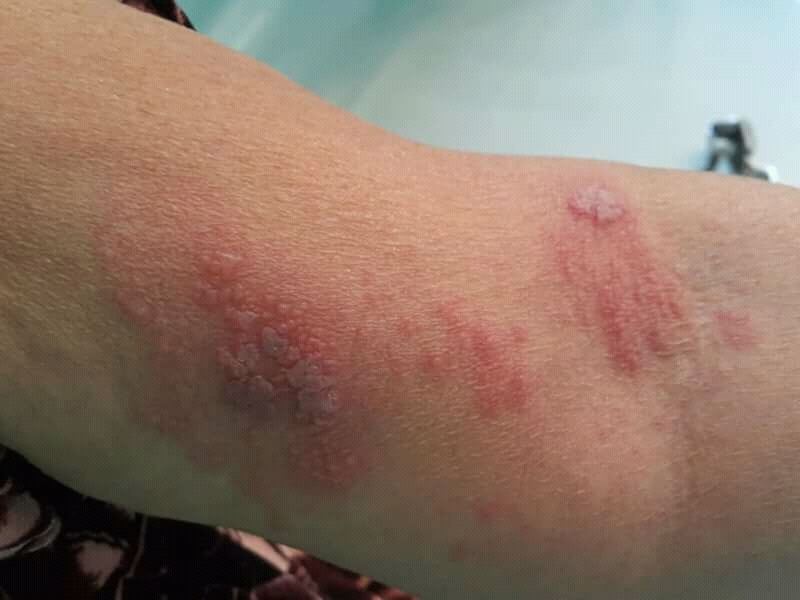
Health systems are expanding vaccination for shingles, flu and respiratory viruses in older adults, where the burden of disease is highest. It is a development that has been building quietly for months, and this week it moved firmly into the mainstream conversation. Specialists in adult immunisation programmes say the latest developments deserve attention precisely because they are measurable: the claims can be checked, the numbers are published, and the people responsible can be asked what happens next.
The story behind the numbers
The research behind the headlines is more nuanced than either enthusiasts or sceptics suggest. The strongest studies are large, follow participants for years and adjust for the obvious confounders — income, existing illness, medication and the healthy-user effect that makes any lifestyle intervention look better than it is. Effects are real but moderate, which is exactly what experienced clinicians expect: health rarely turns on a single change. The practical advice that emerges is correspondingly sensible, emphasising consistency, professional guidance and suspicion of any programme promising dramatic results quickly. Reporting by WHO has tracked the same trend from a different angle, and its conclusions align closely with what local observers describe.
Rural communities face a different version of the same challenge, shaped by distance, infrastructure and thinner local services. On this site, continuing coverage in our Health section has followed adult immunisation programmes as it moved from specialist debate to a topic readers ask about directly, in comments, at events and in the questions they send the newsroom.
Implications for everyday life
Clinicians translate findings like these into advice with three qualifiers: start gradually, adapt to the individual and review after a few months rather than a few days. Public health teams add a fourth — equity. Interventions that only reach the already-healthy widen gaps, so programmes are increasingly designed around workplaces, schools and community venues rather than apps alone. Anyone with an existing condition should treat general reporting as background, not instruction, and raise specifics with their own doctor, who knows the context no study can capture. Public health officials involved in the work emphasise that timelines are realistic rather than heroic, and that the next phase depends as much on public response as on technical or financial capacity.
Sceptics make points that deserve an answer rather than dismissal. Some note that early data can flatter new approaches, that funding shapes which questions get studied, and that media coverage — including coverage of this story — tends to amplify the novel over the representative. Those cautions are well founded, and the most credible voices in the field are usually the first to voice them. The balance of evidence, though, has moved: what was a plausible hypothesis a few years ago is now supported by multiple independent lines of work, and the burden of proof is shifting accordingly. Public opinion is divided, with surveys showing strong support for the goal but disagreement about the method and the timetable.
For now, the direction of travel is clear even if the destination is not. The coming months will show whether early promise turns into lasting change, and this newsroom will keep tracking the data as it arrives.
